
Overview
Parents’ Evaluation of Developmental Status-Revised® (PEDS-R®) is an evidence-based method for detecting and addressing developmental, behavioural and social-emotional/mental health concerns in children under eight years of age.
PEDS-R® is a simple, 12-item questionnaire that is completed by the parent or caregiver. The parent completes the questionnaire and then the practitioner, in partnership with the parent, scores and interprets the parent’s concerns.
Skilful application of PEDS-R® supports the early detection of developmental, behavioural and social-emotional/mental health concerns in babies and children. Early detection of concerns is essential for connecting parents with support.
PEDS-R® helps the practitioner identify whether:
- a child needs a developmental evaluation or mental health assessment
- parents need reassurance or further advice, and if so, on what topics
- a child should be monitored carefully over time to ensure prompt attention for any emerging difficulties.
The 12 questions in PEDS‑R® are designed to help parents share their specific worries and observations about their child’s development and well‑being in a clear, supportive way. Rather than focusing only on the most obvious areas like behaviour or talking, the questions gently guide parents to think about all key domains of development — including language, motor skills, social‑emotional functioning, self‑help, health, and school‑related skills —much like practitioners do when assessing children. This helps practitioners and families work together to understand what’s going well and where extra support might be helpful.
Questionnaire domains
The below 7 domains contribute to identification of developmental delays/disorders:
- expressive language including articulation (talking and making speech sounds)
- receptive language (understanding what you say)
- fine motor (using hands and fingers)
- gross motor (using arms and legs)
- school skills (learning preschool and school skills)
- cognitive (thinking, reasoning and understanding) referred to as global/cognitive
- health concerns.
The below 3 domains contribute to identification of mental health/emotional/behavioural risk
- self-help (learning to do things for themselves
- behaviour, and
- social-emotional (getting along with others).
In addition, PEDS-R® captures other concerns (family challenges). These are not assigned on the PEDS-R® Score Form but still require action such as parenting advice or referral to family support services.
PEDS-R® development
The original PEDS® developmental screening tool was developed in the USA by Dr Frances Page Glascoe PhD, a Professor of Paediatrics at Vanderbilt University. The 10 items on the original questionnaire were chosen on the basis of research data, and the language used in the questions was selected carefully.
PEDS-R® has extended the original 10 questions by adding two questions that prompt for global/cognitive and health concerns and refined the original paths.
Raising parent concerns
PEDS‑R®
- supports decision making
- helps identify when to provide guidance and rescreen and when a referral may be helpful
- makes difficult conversations easier
- acknowledging parents' concerns helps practitioners share sensitive information in a supportive way
- encourages family engagement
- families are more likely to attend well-child visits
- builds strong partnerships
- opens the door for a collaborative, trusting relationship between parents and practitioners
- improves preparation for visits
- practitioners can review concerns in advance, reducing 'oh, by the way' questions
- saves time during appointments
- allows practitioners to focus more directly on the child's needs and next steps.
Parent perspective on PEDS‑R®
Parents are more likely to return for visits when PEDS-R® is used. PEDS-R® validates parents' concerns, and promotes a partnership between parent and professional in understanding the child. This connection builds trust which makes the parent more likely to return.
'I’ve been able to list all the concerns I have at the moment. Thank you so much for this opportunity.' - Parent
Watch a short video featuring Professor Sharon Goldfeld AM, Director of CCCH and paediatrician, public health researcher and policy advisor, explaining the purpose of PEDS-R® and the importance of working collaboratively with parents. Prof Goldfeld has collaborated with Prof Frances Page Glascoe and PEDSTest.com LLC in the US to bring the PEDS® and now PEDS-R® to Australia and New Zealand.
Research
Is the PEDS approach effective?
One of the possible criticisms of developmental screening tools is that they can be performed in isolation, without taking into account the socio-cultural context in which a child grows up, and without systematic input from parents.
There have been concerns that not involving parents actively in the process diminishes the tools’ accuracy and makes it less likely that recommendations will be followed.
The PEDS® approach is based on research findings that tell us, if parents are asked the right questions in the right way, they are very accurate observers of their child's strengths and weaknesses.
Listening to parents’ concerns gives insight into the quality of a child's development, which goes beyond simply checking off milestones. It can help practitioners identify:
- specific areas needing guidance
- such as biting or managing temper tantrums
- developmental challenges
- for instance, a child may say words but not use them effectively to communicate needs.
- behavioural/social-emotional/mental health concerns
- such as difficulty making friends or experiences of being bullied
- effectiveness of previous advice
- repeated concerns over time can show whether earlier support was helpful or if more guidance is needed.
Why was the PEDS revised?
- To improve identification of mental health, social-emotional and behavioural concerns (MEB).
The original PEDS screened for both developmental and behavioural concerns, but PEDS-R introduced revised scoring and interpretation pathways that separately identify Mental Health, Social-Emotional and Behavioural (MEB) risk, Developmental Delay (DD) risk, and combined risk (MEBDD). This allows more specific interpretation and follow-up. - To add two new questions covering domains that were previously under-identified.
PEDS-R expanded the original 10 questions to 12 by adding questions about:
• Global/Cognitive concerns
• Health concerns
Documentation notes that some parents, particularly those from lower-income backgrounds or with English as an additional language, were less likely to raise these concerns unless specifically prompted. The added questions help capture these issues more consistently. - To refine the original PEDS pathways and scoring system.
The revised version includes updated "paths" and interpretation processes, allowing more precise categorisation of developmental, behavioural and mental health risk.
What is the evidence for PEDS® and its revision, PEDS-R®?
Using PEDS® as a developmental screening tool has been validated against standard psychometric tests in a series of studies in the USA. Information published by Glascoe et al. (2013) highlighted the sensitivity (91–97%) and specificity (73–86%) of the PEDS® developmental screening tool.
It also has the advantage of involving parents in the process. The sensitivity of PEDS® in relation to the identification of disabilities i.e. learning, intellectual, language, mental health, autism spectrum disorder and motor disorders was noted to be between 71 and 87%.
In order to test the suitability of PEDS® for use in the Australian context a trial was conducted in selected Victorian preschools. Findings indicated that PEDS® was acceptable to parents of Australian preschool children and indicated that parents reported a prevalence of significant concerns (i.e. children at high and medium risk of developmental problems) that was similar to those in the USA.
PEDS® was re-standardised in 2012. Studies have found no differences in the accuracy of parental concerns on the basis of socio-economic status, number of children in the family, birth order, participation in day care, or parenting experience.
PEDS-Revised or PEDS-R® has extended the original 10 questions by adding two questions that prompt for global/cognitive and health concerns and refined the original Paths. You can find information on ‘How PEDS-R® Works’ on the PEDSTest website. This page provides a Research and Psychometric Summary.
What is the evidence for PEDS® tools in Australia?
In order to test the suitability of PEDS® for use in the Australian context, a trial was conducted in selected Victorian preschools. Findings indicated that PEDS® was acceptable to parents of Australian preschool children and indicated that parents reported a prevalence of significant concerns (i.e. children at high and medium risk of developmental difficulties) that was similar to those in the USA.
PEDS® was re-standardised in 2012. Studies have found no differences in the accuracy of parental concerns on the basis of socio-economic status, number of children in the family, birth order, participation in day care, or parenting experience.
While no further studies have been undertaken in Australia to test the validity of the PEDS-R®, it retains the original 10 questions and simply extends it by adding two questions that prompt for global/cognitive and health concerns.
Format

PEDS-R® combines screening, scoring and interpretation components into a four-page printed, perforated booklet comprising:
- Directions
- Score Form and Interpretation Form
- Practitioner use section for recording Current Findings and Action Steps.
- Response Form
Is there a digital version?
Currently we do not have an electronic application available in Australia to enable parents to complete the response form on-line. The development of an electronic application is something we are exploring. If you would like to know more, have any suggestions or ideas, please reach out to us.
Some services have included the professional-completed components of the PEDS-R® into the electronic client management systems they use through a sub-licence agreement with The Royal Children's Hospital. For further information on this approach please contact us.
Using PEDS-R® in your workplace
Do I need training to use the PEDS-R®?
Practitioner training is essential to ensure PEDS-R® is administered accurately. At the completion of the tutorial, there is a certification test to check knowledge has been accurately obtained and the practitioner has mastered the subject matter. For information, see the resources tab above.
How long will the PEDS-R® take?
- The PEDS-R® takes a few minutes to complete for parents with few or no concerns and around 10 minutes for parents with multiple concerns.
- Scoring takes two minutes if using the print version.
- Additional tasks take five minutes to prepare parent summaries or write referrals.
I’m an educator who spends a lot of time with the child. Can I complete PEDS-R® on my own?
PEDS-R® requires parent and professional collaboration. Many questions, for example, about Self-Help or Health may be difficult for practitioners to answer alone. So, please administer with parents and then add your own concerns.
How does PEDS-R® inform action steps?
Unlike most screening tests, PEDS-R® tells us:
- when to offer parents advice and/or monitoring
- when to refer for early intervention/additional supports
- when to refer for mental health services
- when to refer to other services such as parenting support.
Is the PEDS-R® Response Form available in languages other than English?
PEDS-R® is available in over 60 languages, so you can work with families in the language they are most comfortable with.
To request or purchase a translation, please contact us directly for assistance.
Ordering PEDS-R®
The PEDS-R® comes in packs of 50 booklets. Order by completing the PEDS-R® order form. Please note that PEDS-R® forms are copyright and cannot be photocopied.
What is the cost?
$77 (inc. GST) per pack of 50 booklets. Postage not included.
Licensing
A PEDS-R® sub-license is not required to purchase and use the PEDS-R® booklets with families.
A PEDS-R® sub-license agreement is essential if PEDS-R® materials are to be used:
- to reproduce any of the PEDS-R® materials in child health records
- in a research project
- a population-based survey.
This applies to electronic or paper-based PEDS-R® materials. If you or your organisation would like to know more about a PEDS-R® sub-license agreement, please contact us.
Training
The PEDS-R® training is an online, self-paced tutorial for practitioners. The tutorial provides comprehensive information on PEDS-R®, covering its background, usage and how to score and interpret parent or carer responses.
Through the tutorial, practitioners will learn:
- the background of PEDS-R®
- the components of PEDS-R®, including a detailed walk-through of the PEDS-R® booklet
- how to administer PEDS-R®
- how to score and interpret parent responses
- next steps to take with parents.
Practitioner training is essential to ensure PEDS-R® is administered accurately. At the completion of the tutorial, there is a certification test to check knowledge has been accurately obtained and the practitioner may confidently use PEDS-R® as intended.
You can log out of the tutorial at any stage and come back to complete it at a suitable time. Participants have access to the tutorial for 12 months following registration.
Format: Online, self-paced
Duration: 1.5 hours (including a 20-25 minute certification process)
Cost: $165 (inc GST) per participant
Before completing the training, you can complete the PEDS-R® - Introduction to developmental screening course for free. It provides a background and general introduction to developmental screening and developmental screening tools.
'I've done the PEDS training previously. Do I need PEDS-R® training?'
The PEDS-R® training is important training for both practitioners who have previously completed PEDS® training and practitioners who are new to PEDS-R®. Training is necessary, even for experienced practitioners, to ensure PEDS-R® is administered accurately.
Parent information
PEDS-R® is a developmental screening tool. The PEDS-R® helps practitioners check on your child’s development by learning from any concerns that you might have. You will answer 12 questions about your child’s development and wellbeing.
The PEDS-R® developmental screening tool includes questions about your child’s:
- speech and language
- how your child gets along with others
- learning for school (babies learn from the moment they are born, and it is important to support parents to help children reach their full potential)
- what your child can do for themselves
- social, emotional and behaviour
- how your child uses their hands, fingers, arms and legs
- health, and
- how you think your child is going overall.
The practitioner will then discuss any concerns that you have. They will complete the scoring and provide ideas for any support that could be useful for you and your child.
Completing PEDS-R® supports you to talk about any questions or concerns that you may have about your child’s health, development or wellbeing. This helps the practitioner to give you information or suggest supports related to your concerns, decide if they need further information, and/or make referrals if needed.
You may be asked to complete the PEDS-R® questionnaire for your child at different ages, as part of your appointments or visits with health, early childhood or education practitioners. PEDS-R® may be part of a screening process that is used with young children in your community. Ongoing assessment of your child’s health and development helps both you and the practitioner to keep track of your child’s development and, if needed, organise support early.
Why do we need to check your child’s development?
The first few years of a child's life are a time of fast and important developmental changes. Because young brains grow so quickly, early experiences can easily shape a child's future for better or for worse. If we pick up learning or growing problems early, taking action right away can make a huge difference in helping children succeed as they grow up.
If you would like to learn more about child development and behaviour you can visit these trusted parenting and child health websites:
- Raising Children Network www.raisingchildren.net.au
- Talaris Institute www.parentingcounts.org
- Harvard Center on the Developing Child www.developingchild.harvard.edu
- Zero to Three www.zerotothree.org
Our team
Associate Professor Anita D’Aprano, PEDS-R® Clinical Advisor
Julie O’Brien, PEDS-R® Project Officer
General PEDS-R® enquiries
Centre for Community Child Health
The Royal Children's Hospital
50 Flemington Road
Parkville Victoria 3052 Australia
Email: [email protected]
Tutorial enquiries
For questions or enquiries about the PEDS-R® tutorial, email [email protected].
Register for the tutorial through the MCRI training portal.
Partners and funders
PEDS-R® Authorised Australian version, The Royal Children’s Hospital Centre for Community Child Health, has been adapted with permission from Frances Page Glascoe and PEDSTest.com LLC. ©Copyright 2024.
Resources
Research studies
PEDS® (the version of PEDS® prior to PEDS-R®) has been used in a wide variety of research studies to screen children’s development, either as a means of determining eligibility for a particular study or as an outcome measure.
See examples of PEDS® in research
Parents' Evaluation of Developmental Status-Revised (PEDS-R): Where to next?
For additional information on PEDS-R, you can watch Associate Professor Anita D’Aprano’s presentation at the Maternal Child Conference in Victoria in March 2025.
Early childhood development and early detection
Dr Frances Page Glascoe has co-authored a book titled 'Identifying and Addressing Developmental-Behavioral Problems: A Practical Guide for Medical and Non-medical Professionals, Trainees, Researchers and Advocates' ISBN 9781 7600 19822. This is a valuable resource for practitioners wanting to understand early childhood development and early detection. For more information on how to order this book please contact us.
General FAQs
In the ‘PEDS Brief Administration and Scoring Guide’ there was a table called ‘Categorising Parent Concerns’. We found this really helpful. Can we still access this information?
The PEDS-R® training does include a slide that gives examples of parent comments and the domains they belong to (Figure 1 below). The table from the PEDS Brief Administration and Scoring Guide (Figure 2) can still be used if helpful. An additional resource is the freely downloadable PEDS-R® Handbook, which has many more examples. On pages 4-5 there is a table in the section entitled ‘PEDS-R® Questions: Their Intent, Domains Measured and Descriptions’. Furthermore, in the section PEDS-R® PATH BY PATH (pages 6-13) there are examples of parents’ comments.
 Figure 1. Parent comments and their associated domains.
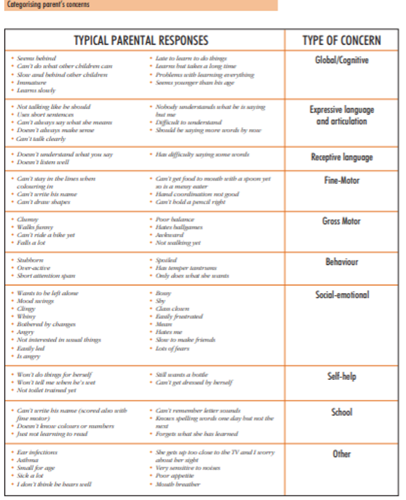
Figure 2. Categorising parent's concerns.
Why are self-help concerns included with MEB Risk?
Children are quite aware when they can’t do what others can do (like tie shoes, button clothes) and this leads to social-emotional issues including poor self-esteem.
When tasks are beyond a child’s current skill level, they may communicate this by disengaging or having difficulty following or refusing to follow directions. Self-help skills reflect children’s growing independence and their ability to engage with everyday guidance from caregivers, and is an indicator of their overall well-being.
Among parents with self-help concerns, 70% had behaviour concerns and 56% had social-emotional concerns. Although self-help concerns are sometimes associated with fine and gross motor concerns, practitioners and parents have an opportunity to mark these separately.
Why are health issues included as a Developmental Delay Risk?
Some serious health issues lead to reduced and limited vitality, frequent school absences, frequent hospitalisations – all of which may be associated with developmental delay. Some health issues are indicators of physical conditions such as syndromes, that can also contribute to developmental delay.
Age calculation and column FAQs
What's the best way to calculate age?
The best way to calculate a child's age is to use the online age calculator on the PEDSTest website or the age calculator built into your service's client management system. The age calculator will ask for the child's birthdate, weeks premature (if any) and will generate the child's Chronological Age and their Adjusted Age to choose the appropriate age column on the PEDS-R® Score Form. The Adjusted Age may or may not be the same as the Chronological Age.
How do I adjust for prematurity?
Chronological age adjustment for prematurity only occurs for children less than 24 months of age and greater than 3 weeks premature. The best way to adjust for prematurity is to use the age calculator at at PEDSTest (link) or the age calculator built into your service's client management system.
Which age column on the Score Form do I follow if a child is at the top of an age range (e.g. 4 1/2 -years-old)?
For ages shown in years, the ' - ' (dash) means 'up to' but not 'through'. So, for example, a 4 year 6 month old is not scored on the 4 - 4 1/2 year column but instead in the 4 1/2 - 6 year column. Similarly, a child who is exactly 6 years 0 months old, is scored on the 6 - 7 year column while a child who is 7 years and 0 months old is scored on the 7 - 8 year column.
Also note that children who are 7 years, 11 months and more than 15 days old, will have a rounded chronological age of 8 years and 0 months. They remain within the age range for PEDS-R and are scored in the 7 - 8 year column.
Scoring FAQs
What do I do when a parent raises questions instead of answering PEDS-R® questions?
If parents write a question such as, 'I don’t know what he should be doing at his age', mark this as a concern on the PEDS-R® Response Form. Such parents need developmental and behavioural guidance and monitoring, just for starters.
If administering PEDS-R® by interview and parents ask 'What do you mean?', do not give examples. These distract from the 'big picture' summary we want parents to provide. Just say, 'I’d like to know what you think – whatever comes to mind.' Only after PEDS-R® is scored should practitioners give advice on child development.
Where should I note concerns about hyperactivity/ADHD, or medical/genetic conditions?
Write these in the space for Question 11. Then put a tick in the circle for health concerns.
What do predictive and non-predictive concerns mean?
Non-predictive concerns are those not currently associated with a diagnosis or need or eligibility for support services. Predictive concerns are those associated with a diagnosis, need or eligibility for support services.
These change by children’s age as shown on the PEDS-R® Score Form. For example, Gross Motor concerns are non-predictive in very young children because parents are usually asking about expected milestones, such as at what age should a child sit up, stand, walk. At older ages, Gross Motor concerns become predictive of potential difficulties.
What if I notice a significant concern but the domain is non-predictive or a child scores on a lower risk Path?
In the example of non-predictive Gross Motor concerns above:
- If practitioners identify conditions such as spasticity, hypotonicity, cerebral palsy, etc., these should be added to Health concerns before scoring.
- Practitioners may decide, at any visit, to refer whether or not PEDS-R® shows high risk.
- Practitioners should always refer when PEDS-R® so indicates.
What is the difference between 'A little concerned' and 'Concerned'?
There is no difference when scoring PEDS-R®: Either response is considered a concern. Both options are included to discourage parents from circling “Not concerned” when they aren’t sure whether they should be concerned.
In other words, parents often observe differences between their child and others, but may not know initially whether or not these differences should be considered troubling. So the 'A little concerned' response option helps parents express what they’ve noticed, even if they aren’t sure whether or not to be 'Concerned'.
What do I do if a parent raises a concern on the first question but then circles 'Not concerned' on a later question associated with the domain mentioned?
Cross out 'Not Concerned' and circle 'Concerned' on the PEDS-R® Response Form for the domain mentioned. For example, if a parent writes on Question #1, 'I’m worried about his talking,' but circles 'Not concerned' for the Question #2 (about Expressive Language), cross out 'Not concerned' and circle 'Concerned.'
If parents did not write any words on PEDS-R®, can I still score it?
No. If parents did not write any comments, only wrote 'No' or skipped responses, then re-administer PEDS-R® by interview. A lack of comments from a parent may indicate that language or literacy barriers are present.
Practitioners should ask which language parents prefer before presenting PEDS-R® in writing. The PEDS-R® response form is available in over 60 languages. Practitioners should also ask, 'Would you like to complete this on your own or have us go through it with you?'
If English is an additional language, and parents prefer to go through it with you, consider using an interpreter.
What if my observation differs from a parents’ concerns? Should I change their concerns?
It is not unusual for parents and practitioners to sometimes see a child’s development differently. These different perspectives can be very helpful for early understanding and support. For this reason, collaboration is crucial.
Parents know their child best. They may raise concerns about behaviours that practitioners recognise as part of typical development. Even so, parents’ observations are important and deserve thoughtful attention. These moments can also be opportunities to share helpful information about child development.
PEDS-R® helps guide next steps. The results provide direction on whether it may be helpful to monitor development, offer guidance, or consider further support.
Parents and practitioners see children in different settings. Practitioners may observe children mainly during brief visits, while parents see them across many daily routines. PEDS-R® helps practitioners learn from parents about how children function in a variety of environments.
If your perspective differs from a parent’s concern, include their concern when scoring rather than removing it. Parents’ insights remain valuable.
Practitioners are also encouraged to add their own observations to the PEDS-R® Response Form before scoring. For example, parents may notice excessively repetitive play but may not know this could be a sign of autism. If practitioners notice something that may need further attention, they can note it in the relevant Response Form question or the Health question. Working together in this way helps ensure that both parent and professional perspectives contribute to understanding the child and identifying the best supports.
I addressed the parents’ concerns – should I change the PEDS-R® results?
No. It’s important to keep parents’ original comments and response choices exactly as they were recorded on the PEDS-R®.
Even if you’ve already provided guidance or support, those responses help track whether concerns change over time. Plan to rescreen in about 6–8 weeks to see how things are progressing. Comparing the new results with the previous PEDS-R® can show whether concerns have resolved or are still present.
This approach helps practitioners and families see what’s working and decide together on next steps.
What happened to Path D? Why are Path D and Path E shown as Path D/E in PEDS-R®?
In the PEDS, Path D helped alert practitioners to possible administration issues — for example, if the questionnaire was completed in the wrong language, if the respondent was not the child’s main caregiver, or if literacy challenges made it difficult to provide written comments.
With PEDS-R®, these situations are addressed through careful administration, so a separate Path D is usually not needed. Instead, Path D and Path E are combined.
When you see a Path D/E result, it’s a helpful reminder to pause and check that the questions were clearly understood and that the form was completed as intended. If needed, you can review the questions together with the parent or caregiver to ensure their perspectives are fully captured.
Taking this extra step helps ensure that families’ insights are accurately reflected and that the results provide the most helpful guidance for next steps.
I’m an educator who spends a lot of time with the child. Can I complete PEDS-R® on my own?
PEDS-R® requires parent and practitioner collaboration. Many questions, for example, about Self-Help or Health may be difficult for Practitioners to answer alone. So, please administer with parents and then add your own concerns.
Our staff administer PEDS-R®, score it, and then only show the Paths/Risk levels in the electronic record – not parents’ actual comments.
Ideally parents’ comments should be included in each child’s electronic record. The PEDS-R® booklet (especially the final two pages) needs to be included in each child’s electronic record to show that not only was PEDS-R® administered but what actions were taken in response to parents’ concerns.
Decisions and Action Steps FAQs
Do specific concerns indicate the type of issue?
Sometimes they do, but not always. For example, concerns about a child’s expressive language (which is one of the most common worries parents share) can be linked to speech-language delays—but they can also be related to conditions like autism spectrum disorder or intellectual disabilities.
Because of this, if PEDS-R® suggests a referral is needed, follow-up assessment should cover a broad range of developmental areas to get a full picture of the child’s strengths and needs.
What if a child has lots of psychosocial risks for future concerns but appears OK for now?
You can:
- provide guidance to the parent on what the next stages of development are, what to look for and ways parents can interact with their child to enhance development
- encourage parents to enrol in local programs (see guidance for each Path)
- rescreen in 6 – 8 weeks to make sure child and parents are making progress
- refer to parenting program or other relevant program.
The families I refer for services don’t always follow through. What can I do?
It’s common for families to face challenges in following up on referrals. Sometimes this is because of language differences, transportation issues, work schedules, or uncertainty about the process.
Here are some ways to support families and help them connect with services:
- Follow up gently
- Check in after 6–8 weeks to see how things are going and offer encouragement.
- Build strong relationships
- Get to know families and their unique situations so you can understand any barriers or concerns.
- Make referrals 'warm'
- Consider a 3-way call with the family and the referral source to explain the next steps together.
- Address practical barriers
- Help families with transportation, scheduling, or financial concerns whenever possible.
- Use interpretation services
- Encourage referral sources to provide language support if needed.
- Flexible appointment options
- Ask if appointments can be conducted in settings that work best for families, such as their home.
What if the parent reporting on PEDS-R® is not actually the main caregiver and doesn’t know much about their child – meaning I’m not confident in the results?
Sometimes older siblings or another relative who isn't the main caregiver, accompany children to appointments. In such cases, you can:
- send a copy of PEDS-R® home for the main caregiver to complete
- call the main caregiver and administer PEDS-R® over the phone
- offer to make another appointment with the main caregiver.
Unique populations and translation FAQs
How are PEDS® Tools translated, and how do you make sure the translations work well?
PEDS® Tools go through a careful translation process to make sure they are accurate and meaningful for families from different cultural and linguistic backgrounds.
Translations start with a professional translation service, then are reviewed by multi-lingual health professionals. For widely spoken languages with many dialects—like Spanish—teams representing different regions (e.g., Mexico, Argentina, Spain) help ensure the wording works for everyone.
Some languages need separate translations for different speaker groups (e.g., Portuguese vs. Cape Verdean, French vs. Haitian-Creole). The PEDSTest team also listens to feedback from users. For example, the Chinese translation of 'concerned' was adjusted because the original wording caused confusion. 'Worried' was a closer match to the English meaning.
Translations are regularly updated to reflect language changes over time, migration patterns, and dialect differences. This careful process helps make sure parents’ responses reflect their true concerns and that PEDS® results are meaningful across languages and cultures.
What do we do if we see a family who speaks a language for which there is no translated Response Form?
The English questions in the PEDS-R® Response Form are written at a third-grade level, making translation by an accredited interpreter a relatively straightforward process.
We recommend using an accredited interpreter as part of your consultation with the family to translate the PEDS-R® questions into the relevant language. Using an interpreter supports the family to fully understand the questions and share their child’s experiences accurately, helping you capture their insights and concerns effectively.
Some families are not literate in their own language – what do we do?
For families who are not literate, we recommend using an accredited interpreter to:
- read the questions aloud to the family
- record the family's response word-for-word
- translate the responses into English for scoring.
Q. Can I use PEDS-R® with new foster or adoptive parents?
Yes! Foster and adoptive parents often have valuable experience with children and can provide important insights when completing PEDS-R®.
Children in out of home care are at higher risk for developmental or health concerns, so it's especially important for them to have evaluations by health practitioners. In many parts of Australia, specialised programs support these assessments - like Pathway to Good Health in Victoria or Child and Youth Health Services in QLD. It's worth checking if the child has already been referred to such a program.
What can I expect if administering PEDS-R® to families seeking asylum?
Families in this situation may feel cautious about sharing health problems or developmental-behavioural concerns, sometimes worrying it could affect their application. Developing a relationship is essential. It can be helpful to repeat PEDS-R® after families have had time to settle, so you get a clearer picture of the child's needs and strengths.
Can I use PEDS-R® when children have chronic illness?
Yes. Just because a child is chronically ill does not mean they do not need to be screened. Screenings, and screenings over time, allows insight to how they are growing developmentally, socially/emotionally, mentally, and behaviourally. It also allows practitioners to see children’s areas of strengths and their challenges.
PEDS-R® in research
I’d like to put all the PEDS-R® questions in my research protocol along with the other measures I’m using. Is that OK?
We support the use of PEDS-R® in research, however, it is not permitted to use any of the PEDS-R® questions in research without permission.
We do offer preferential rates for researchers from research institutes or not-for-profit organisations, so please contact us to discuss use of the PEDS-R® in research protocols.
My research involves only very young children. May I use only some of the PEDS-R® questions?
No. All PEDS-R® questions are needed. Even the question about preschool and school skills when asked of parents with infants, offer important information about what parents are doing at home to promote development. For example, use of flash cards with very young children alerts practitioners to the need to guide parents into interactions offering more appropriate learning activities.
Where can I access more information on the PEDS-R® psychometrics?
You can learn more about how PEDS-R® works on the PEDSTest website. This website also provides a Research and Psychometric Summary.
Contact us
For more information on PEDS-R® email us at [email protected].
'Bringing parents’ voices to the table is so important; they are the experts of their children. The beauty about the PEDS-R® is that it’s really a set of questions that is scaffolding for parents to think about how to talk about their children and their concerns.'